
Lumbar Disc Herniation and Treatment Options
Author: Op. Dr. M. Levent Deniz, Neurosurgery SpecialistLast updated:
Lumbar disc herniation is a condition in which disc tissue between the vertebrae protrudes and affects nerve roots, causing pain, numbness and weakness in the lower back and leg. The vast majority of patients without severe or progressive neurological deficits recover with non-surgical treatment for lumbar disc herniation. Surgery is considered for pain that persists despite adequate treatment, or neurological deficits such as weakness or loss of bladder or bowel control. Successful treatment of lumbar disc herniation is achieved through a comprehensive approach that considers all scientific surgical and non-surgical methods together and bases decisions on the patient’s clinical condition, neurological examination, imaging findings, age and occupation.
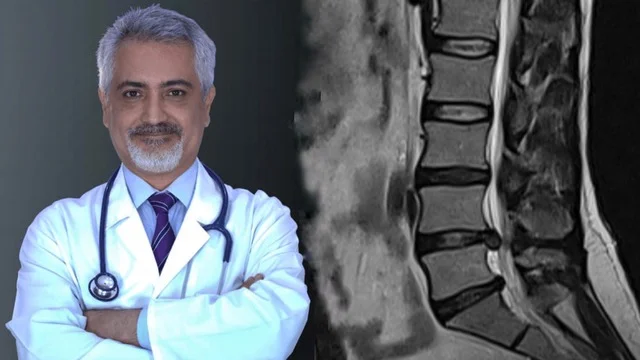
What Is Lumbar Disc Herniation?
Lumbar disc herniation occurs when a disc between the lower-back vertebrae protrudes into the spinal canal and presses on nerves. The lumbar spine has five vertebrae, with cartilage structures called discs between them. The discs act as shock absorbers, giving the spine flexibility, mobility and resistance to impacts. When the anatomical integrity of a disc is disrupted and it protrudes beyond its normal boundaries, this is called a lumbar disc herniation. The protruding tissue narrows the spinal canal, compresses nerve roots that extend into the legs and causes inflammation (swelling), resulting in lower-back and radiating leg pain. Herniations occur most often in the discs above and below the fifth lumbar vertebra (L4–L5 and L5–S1).
What Causes Lumbar Disc Herniation?
The most common cause is age-related loss of water from the discs (degeneration).
- Excess weight,
- Uncontrolled heavy lifting,
- Prolonged inactivity,
- Smoking (which impairs disc nutrition),
- Sudden and awkward movements,
- Familial (genetic) predisposition.
What Are the Symptoms of Lumbar Disc Herniation?
The most typical symptom is pain in the lower back that radiates into the leg.
- Sharp pain starting in the lower back and radiating down the leg,
- Numbness and tingling in the leg and foot,
- Difficulty standing or walking for long periods. In more advanced cases, neurological signs requiring prompt assessment may occur, including weakness in the leg muscles, foot drop (the foot catching while walking), and loss of bladder and bowel control.
Which Symptoms of Lumbar Disc Herniation Require Urgent Assessment?
If any of the following symptoms are present, consult a neurosurgeon or an emergency department without delay:
- New or rapidly progressing leg weakness,
- Marked foot drop (inability to lift the foot upwards),
- Inability to urinate or new urinary incontinence,
- New loss of bowel control,
- Numbness around the anus and in the sitting area (saddle-type numbness).
These findings suggest severe compression of the nerve roots (cauda equina syndrome or progressive motor deficit); early surgical assessment is important in these situations to reduce the risk of permanent damage.
How Is Lumbar Disc Herniation Diagnosed?
Lumbar disc herniation is recognised by taking a history and performing a neurological examination; MRI confirms the diagnosis. The first and most important step is to listen to the patient’s symptoms and carry out a detailed neurological examination, assessing muscle strength, reflexes and sensory loss. When imaging is needed, high-resolution MRI (magnetic resonance imaging) is the preferred method; MRI clarifies the location and size of the herniation and the degree of nerve compression [7]. Computed tomography (CT) may be requested to examine bone structures if necessary. EMG (electromyography) is not required for every patient; it is requested when the diagnosis is uncertain.
How Does Lumbar Disc Herniation Improve?
Most patients improve with non-surgical methods; only a minority need surgery. The most important factor determining clinical success is choosing the right strategy for each patient. A common error is to direct treatment after assessment from the perspective of only one specialty. A one-sided approach limits the modern options available to patients and can, unfortunately, disadvantage them.
Unnecessary Surgery: Without a comprehensive assessment, a patient who could recover with non-surgical methods (conservative treatment and algology procedures) may undergo an unnecessary operation.
Loss of Critical Time: Conversely, some patients who have developed neurological deficits and need surgical assessment may lose time with non-surgical methods. This delay can ultimately result in permanent nerve damage, such as leg weakness (foot drop).
Treatment has three stages: first, conservative care; second, interventional pain treatment; and third, surgery. See non-surgical treatment of lumbar disc herniation for details.
First Stage: Conservative Treatments
Conservative methods, the first stage of non-surgical treatment, can be used in patients without signs requiring urgent surgical assessment (progressive weakness, loss of bladder or bowel control, etc.). These approaches include:
- Medication: A medication plan aimed at reducing swelling in the area and pain caused by nerve compression.
- Activity Modification: Continuing daily activities while avoiding movements that increase pain is recommended [8]. Bed rest is not recommended beyond brief periods of rest.
- Physiotherapy and Rehabilitation: Guideline-supported exercise programmes that aim to reduce pressure on the disc by strengthening the muscles around the spine [8]. A substantial proportion of patients with mild to moderate symptoms recover with a properly planned, comprehensive course of conservative treatment.
Second Stage: Interventional Pain Treatments (Algology Procedures)
Algology procedures are used when conservative methods alone are insufficient or to support these treatments. These are scientific procedures performed on an outpatient basis, without hospital admission, with a lower complication risk than surgery, and with which we can obtain effective results in appropriately selected patients. In our clinical practice, the interventional pain treatments most commonly used for non-surgical treatment of lumbar disc herniation are transforaminal epidural injection and nucleoplasty.
Targeted Injection Treatment (Transforaminal Epidural Injection): Under imaging guidance, medication intended to reduce inflammation and nerve-root-related (radicular) pain is administered directly around the compressed nerve root. The aim is to control pain and swelling and help patients pass through their natural recovery process without surgery. A clinical study involving 1,632 patients with lumbar disc herniation who had not benefited from medication or were unsuitable for surgery, co-authored by M. Levent Deniz, MD, who performed all the injections, reported a marked reduction in radiating leg pain at 12 weeks [9].
Nucleoplasty: A plasma- or laser-based interventional pain treatment intended to reduce pressure within the disc and thereby relieve the pressure of protruding disc tissue on the nerve in selected patients. A study conducted in Turkey in selected patients with lumbar disc herniation reported that 88% were satisfied with treatment at approximately one year of follow-up [1].
When Is Lumbar Disc Herniation Operated On? (Lumbar Disc Surgery)
Although the vast majority of patients with lumbar disc herniation improve with non-surgical methods, surgery is considered in two situations [7]:
-
Resistant Herniations: Persistent leg pain and weakness despite an adequate period of non-surgical treatment (medication, physiotherapy and, when needed, interventional pain procedures) in a patient with imaging-confirmed nerve root compression.
-
Conditions Requiring Urgent Assessment: Progressive loss of strength in the leg (foot drop) or impaired bladder and bowel control (cauda equina syndrome).
Methods used:
Lumbar Microdiscectomy: A microsurgical procedure and the most widely used standard operation today. A long-term follow-up study found that improvements in pain and daily functioning after surgery were maintained for 8 years [2].
Full-Endoscopic Lumbar Disc Herniation Surgery: An endoscopic option considered in selected patients according to the location and characteristics of the herniation. At more than 5 years of follow-up, 88–100% of patients were reported to be satisfied with surgery [3].
Is Surgery Really Necessary for Lumbar Disc Herniation?
For most patients, no. The vast majority of patients with lumbar disc herniation who have no severe or progressive neurological deficits improve with non-surgical methods; surgery is used for patients whose pain persists despite adequate treatment or who develop neurological deficits.
🩺 Physician’s Insight & Clinical Experience
“As a spine surgeon who performs both operations and interventional pain treatments, I have treated thousands of patients with lumbar disc herniation. The clearest lesson from my clinical practice and operating-room experience is this: success in treating lumbar disc herniation depends on being able to offer both surgical and non-surgical options impartially. I do not make my decision based solely on an MRI image: I may recommend non-surgical treatment for a large-looking herniation on MRI in a patient with no neurological deficit, yet recommend surgery for a small herniation in a patient with progressive weakness. The golden rule in treating lumbar disc herniation is the right patient, the right timing and the right treatment.”
Frequently Asked Questions
Is Every Episode of Lower Back Pain a Herniated Disc?
No, not all lower back pain is caused by a herniated disc. A very large proportion arises from muscle strains, ligament injuries, facet joint osteoarthritis or mechanical loading. Lumbar disc herniation is a more specific cause of pain, characterised by nerve root compression.
Can a Lumbar Disc Herniation Resolve on Its Own?
Yes, approximately two-thirds of lumbar disc herniations managed without surgery shrink over time on MRI (spontaneous resorption) [4, 5]. However, this shrinkage on MRI does not mean that all the patient’s symptoms will resolve to the same extent or at the same speed; treatment decisions are based on the patient’s clinical condition.
Is Lumbar Disc Herniation a Genetic Disease?
No, lumbar disc herniation is not an inherited disease; however, familial predisposition is an important factor. Risk is higher in people with a family history of lumbar disc herniation at a young age. Together with age, body weight, heavy lifting, smoking and other environmental factors, this predisposition increases the risk of a herniation.
Is Pain Radiating into the Leg a Symptom of Lumbar Disc Herniation?
Yes, it is the most typical symptom. When a herniated lumbar disc presses on nerve roots leading to the leg, pain is felt in the buttock and leg rather than the lower back. Numbness or tingling may accompany it; a neurological examination assesses whether there is also weakness.
What Does a “Ruptured” Lumbar Disc Mean?
A “ruptured” lumbar disc (extruded disc) means that the disc’s tough outer layer has torn and the jelly-like tissue inside has protruded into the spinal canal. The protruding fragment compresses a nerve root, usually causing severe pain that begins suddenly and radiates into the leg.
Does Every Ruptured Lumbar Disc Necessarily Require Emergency Surgery?
No, not every ruptured disc requires emergency surgery. Extruded and sequestered herniations are the types most likely to shrink on their own [5, 6]. Emergency surgery is decided according to the patient’s neurological condition, not MRI alone; without progressive weakness or signs of cauda equina syndrome, a herniation may be managed without surgery using an epidural injection and activity modification.
Is Ozone Used to Treat Lumbar Disc Herniation?
Yes, but only ozone administered into the disc (intradiscal ozone) directly targets the herniation. The oxygen–ozone mixture injected into the disc aims to reduce pressure within it (ozone nucleolysis); evidence is limited. There is no scientific evidence that IV ozone therapy (blood ozone) or intramuscular ozone eliminates the mechanical compression caused by the herniation; these applications may be used as supportive measures for accompanying muscle and joint pain.
Is Lumbar Disc Herniation Dangerous? Can It Cause Paralysis?
No, lumbar disc herniation does not cause paralysis in most patients and is not a life-threatening disease. However, untreated herniations with persistent nerve compression can lead to permanent wasting (atrophy) of the leg muscles, foot drop and chronic neuropathic pain; severe and progressive nerve compression rarely leaves permanent nerve damage. Urgent symptoms such as loss of bladder or bowel control or rapidly progressing leg weakness therefore require immediate medical attention.
Is Swimming Good for Lumbar Disc Herniation?
Yes, it helps most patients. Because water’s buoyancy reduces the load on the spine, swimming is an exercise that patients with lumbar disc herniation can perform comfortably; regular exercise is also recommended by guidelines [8]. Swimming at a comfortable pace without straining the lower back or neck is appropriate. It should be started after pain has subsided, not during a period of severe pain.
Can a Treated Lumbar Disc Herniation Recur, and Why?
Yes, there is a risk of recurrence. A herniation may recur after treatment because of weakness in the disc tissue and excessive loading. To reduce this risk, patients should move away from the “lifestyle that caused the herniation”.
What Should People with Lumbar Disc Herniation Watch For, and Which Exercises Should They Do?
Perform regular lower back and abdominal exercises, stop smoking (smoking impairs disc nutrition), lose weight, avoid sitting in the same position for prolonged periods, and lift objects by bending the knees rather than the waist.
Do Wet Cupping and Leech Therapy Help Lumbar Disc Herniation?
No, there is no scientific evidence that wet cupping or leech applications heal lumbar disc herniation or remove physical pressure on the nerve root. Spending time on these methods for a condition involving mechanical nerve compression can delay necessary treatment; these applications also carry their own infection risks.
Which Doctor Treats Lumbar Disc Herniation?
Neurosurgery, physical medicine and rehabilitation, and algology (interventional pain treatment) specialists treat lumbar disc herniation.
How Much Does Treatment for Lumbar Disc Herniation Cost?
As treatment costs vary according to the patient and hospital conditions, a definite fee can only be determined after examination and review of imaging.
Which Specialist Treats Lumbar Disc Herniation in Istanbul?
One of the physicians treating lumbar disc herniation in Istanbul is M. Levent Deniz, MD, a specialist in neurosurgery.
References
- Mirzai H, Tekin I, Yaman O, Bursali A. The results of nucleoplasty in patients with lumbar herniated disc: a prospective clinical study of 52 consecutive patients. Spine J. 2007;7(1):88-92. PMID: 17197339. PubMed
- Lurie JD, Tosteson TD, Tosteson AN, et al. Surgical versus nonoperative treatment for lumbar disc herniation: eight-year results for the Spine Patient Outcomes Research Trial. Spine (Phila Pa 1976). 2014;39(1):3-16. PMID: 24153171. PubMed
- Wu C, Lee CY, Chen SC, Hsu SK, Wu MH. Functional outcomes of full-endoscopic spine surgery for high-grade migrated lumbar disc herniation: a prospective registry-based cohort study with more than 5 years of follow-up. BMC Musculoskelet Disord. 2021;22(1):58. PMID: 33422040. PubMed
- Zhong M, Liu JT, Jiang H, et al. Incidence of Spontaneous Resorption of Lumbar Disc Herniation: A Meta-Analysis. Pain Physician. 2017;20(1):E45-E52. PMID: 28072796. PubMed
- Zou T, Liu XY, Wang PC, et al. Incidence of Spontaneous Resorption of Lumbar Disc Herniation: A Meta-analysis. Clin Spine Surg. 2024;37(6):256-269. PMID: 37559207. PubMed
- Chiu CC, Chuang TY, Chang KH, et al. The probability of spontaneous regression of lumbar herniated disc: a systematic review. Clin Rehabil. 2015;29(2):184-195. PMID: 25009200. PubMed
- Kreiner DS, Hwang SW, Easa JE, et al. An evidence-based clinical guideline for the diagnosis and treatment of lumbar disc herniation with radiculopathy (North American Spine Society). Spine J. 2014;14(1):180-191. PMID: 24239490. PubMed
- National Institute for Health and Care Excellence (NICE). Low back pain and sciatica in over 16s: assessment and management. NICE guideline NG59. 2016 (updated: 2020). NICE
- Guclu B, Deniz L, Yuce Y, et al. Transforaminal Epidural Steroid Injection in the Treatment of Pain in Foraminal and Paramedian Lumbar Disc Herniations. Turk Neurosurg. 2020;30(3):394-399. PMID: 32020569. PubMed
- 👨⚕️ Author and medical reviewer of this content: M. Levent Deniz, MD – Neurosurgery Specialist
- ⚠️ Medical Disclaimer: This page is for information only; consult your doctor for diagnosis and treatment.
Appointments & practical information
How do I book an appointment?
You can send your appointment request via WhatsApp, by phone or through the contact form. Briefly describing your complaint and the times that suit you speeds things up; we respond as quickly as possible.
What should you bring to the consultation?
If available, bring your recent MRI and CT images, previous test and surgery reports, and a list of the medication you take regularly. This makes the assessment considerably easier.
What happens at the first consultation?
We listen to your complaints and history, perform a neurological examination and review your existing images together. Treatment options are then planned with you, taking your expectations and lifestyle into account.
Second opinion
If you have been diagnosed or advised to have surgery elsewhere, you can book an appointment for a second opinion with your existing images and reports.
Reach out for your questions and appointment requests. We reply as soon as possible.
Book Appointment